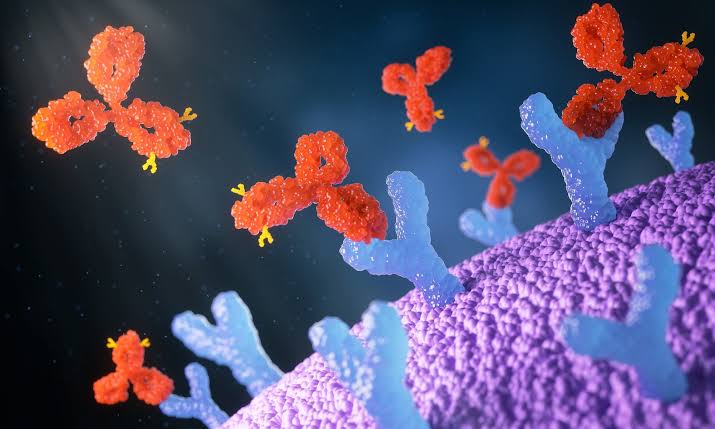
Biologic therapies can trigger immune responses when patients recognise therapeutic proteins as unfamiliar molecular structures. Some patients develop anti-drug antibodies that bind treatment and may alter exposure, biological activity, efficacy, or safety. An ADA assay detects drug-reactive binding antibodies, while additional testing evaluates their specificity and functional consequences. This layered strategy connects immune responses with pharmacokinetics, efficacy, safety, treatment persistence, and clinical timing. Appropriate sampling and validated assay performance are essential for interpreting treatment-emergent responses throughout clinical biologic drug development.
Why Does Immunogenicity Testing Matter During Biologic Development?
Immunogenicity Testing matters because anti-drug antibodies can alter exposure, therapeutic activity, or treatment safety profiles. Binding antibodies may increase drug clearance, lowering circulating concentrations without directly blocking the therapeutic mechanism itself. Other responses may alter distribution, form immune complexes, or coincide with hypersensitivity or infusion-related reactions.
FDA and EMA guidance support risk-based immunogenicity assessment integrated throughout clinical development programmes and interpretation. The phrase immunogenicity ADA may appear in project terminology, although ADA testing represents only one component.
How Does a Tiered ADA Testing Strategy Work?
Regulatory guidance supports tiered testing that separates initial detection from confirmation, characterisation, and functional assessment.
- Screen samples using a sensitive method designed to detect possible anti-drug antibody responses after treatment exposure.
- Confirm reactive samples by demonstrating that observed signals are specifically inhibited by the therapeutic drug itself.
- Determine antibody titre in confirmed samples to describe the relative magnitude of the detected antibody response.
- Evaluate neutralising activity when appropriate using a neutralising antibody assay aligned with the therapeutic mechanism of action.
This sequence reduces false-positive interpretation while separating drug binding from antibodies with potential functional consequences.
How Are ADA and Neutralising Antibody Assays Different?
How Are ADA and Neutralising Antibody Assays Different?
ADA and neutralising antibody assays evaluate different aspects of the immune response against a therapeutic biologic.
- An ADA assay detects antibodies that bind specifically to the therapeutic drug within a patient sample.
- A NAb assay determines whether detected antibodies interfere with the drug’s intended biological activity.
- Neutralising testing is typically performed on confirmed ADA-positive samples when functional impact requires further assessment.
- Cell-based assays evaluate pathway-relevant functional effects when living cells reproduce an appropriate part of drug activity.
- Competitive ligand-binding formats assess whether antibodies block specific molecular interactions involved in the therapeutic mechanism.
Together, these results help researchers assess whether an immune response affects exposure, efficacy, safety, or treatment activity.
Must Read: How Biochemical Assays Support Pharmaceutical Drug Discovery
What Can Cause an ADA Assay to Miss Antibodies?
Circulating therapeutic drug can bind available antibodies and prevent their detection during the analytical reaction. High target concentrations, matrix components, low antibody affinity, or unsuitable sampling times may also reduce detection.
- Drug tolerance describes how much circulating therapeutic remains compatible with detecting anti-drug antibodies under defined conditions.
- Cut points distinguish expected background reactivity from samples requiring confirmation under established analytical assay conditions.
- Baseline samples identify pre-existing reactivity and support accurate classification of treatment-emergent or treatment-boosted antibody responses.
Why Does Sampling Time Matter for ADA Detection?
Sampling time matters because circulating therapeutic concentrations can mask antibodies and lower apparent ADA detection rates. Baseline samples establish pre-existing reactivity, while later collections identify treatment-emergent or treatment-boosted immune responses accurately.

Schedules should consider dosing frequency, drug half-life, expected antibody kinetics, and validated assay drug tolerance. Samples collected soon after dosing may contain enough circulating therapeutic to interfere with antibody detection.
Later collections may reveal persistent responses previously masked during periods of higher circulating drug exposure. Symptom-driven sampling can also support assessment when clinical findings suggest unscheduled immune responses during treatment.
How Are Immunogenicity Assays Validated?
An immunogenicity assay requires validation matching its intended purpose, therapeutic characteristics, matrix, and development stage. FDA guidance identifies cut points, sensitivity, drug tolerance, specificity, selectivity, precision, and related validation characteristics.
Validation should also consider reproducibility, robustness, critical-reagent stability, and relevant concentrations of circulating therapeutic drug. Specialised immunogenicity testing services may include assay development, validation, sample analysis, and study-phase interpretation support.
Platform selection should reflect therapeutic properties and study requirements rather than applying one universal format across biologics.
How Should ADA Results Be Interpreted With Clinical Data?
ADA incidence alone does not establish clinical significance because antibody responses vary in magnitude, persistence, and function. Researchers therefore interpret immunogenicity testing alongside drug concentrations, dosing history, efficacy measures, and clinical safety findings.
A confirmed response accompanied by reduced exposure may indicate increased clearance, but interpretation requires complete study evidence. Positive neutralising results become more informative when functional loss aligns with pharmacokinetic, efficacy, or safety changes.
Separate programmes may use LC-MS Method Development for exposure analysis when mass-spectrometric bioanalysis suits the therapeutic. However, exposure measurement and ADA testing address different questions and should not substitute for one another.
Summary
ADA assays provide the first analytical layer for detecting drug-reactive antibodies during biologic immunogenicity assessment programmes. Tiered testing then confirms specificity, characterises response magnitude, and evaluates neutralising activity when scientifically appropriate. Reliable interpretation requires suitable sampling, validated assay performance, and consideration of circulating drug interference during testing. Clinical significance emerges by integrating immunogenicity findings with pharmacokinetics, efficacy, safety, and treatment timing across development. Together, these data help development teams understand whether immune responses influence therapeutic exposure, function, or patient outcomes.


